
From Instrument-Mounted Demonstrations to In-Vivo Execution: Learning Bimanual Laparoscopic Appendectomy Without Robot-Collected Demonstrations

Dongho Yee*1,2,4,5, Juahn Oh1,2,10, Jinseok Lee2,4, Jiyul Lee1,2,3, Yechan Seo1,2,3, Seong Jeong1,2,3, Minsung Kim1,2,4, Seonho Shim2,11, Younghoon Noh2,4, Hyuk Choi1,2,3, Youngbin Kong1,9, Kyu Eun Lee†6,7, Hyoun-Joong Kong†1,3,8

1Department of Transdisciplinary Medicine, Seoul National University Hospital   2Rosota Inc.   3Department of Medicine, Seoul National University College of Medicine   4Department of Mechanical Engineering, Seoul National University   5Department of Computer Science and Engineering, Seoul National University

6Department of Surgery, Seoul National University Hospital   7Department of Surgery, Seoul National University College of Medicine   8Institute of Convergence Medicine with Innovative Technology, Seoul National University Hospital   9Interdisciplinary Program in Medical Informatics, Seoul National University College of Medicine   10Eulji University College of Medicine   11Department of Mechanical Engineering, Chungang University

*First author    †Corresponding authors

arXiv preprint, September 2026  ·  Submitted to IEEE ICRA 2027

Rosota Seoul National University Hospital, Department of Transdisciplinary Medicine

Supplementary video submitted with the paper (2 min 41 s). Demonstrations recorded on a surgeon's own hand-held instruments were sufficient to train, select and deploy a bimanual policy that completed appendectomies with electrosurgery in three of four live rabbits.

Abstract

Most minimally invasive surgery is still performed with hand-held laparoscopic instruments, and the surgeon's instrument kinematics are lost when the operation ends; only the endoscope video is kept. This paper presents an end-to-end pipeline that captures this motion in the operating room and uses it to train a surgical robot policy, validated on live animals. We introduce a surgical instrument-state logger that mounts on the shaft of a standard laparoscopic instrument and recovers its pose and jaw state from an inertial sensor, a time-of-flight sensor and a Hall sensor, with no external camera or tracker. A data pipeline measures the latency of every sensor channel against a robot ground truth and aligns the channels before forming observation–action pairs. On these demonstrations we train a diffusion policy with a fine-tuned DINOv3 backbone, selecting its design by closed-loop rollouts in a physics simulator reconstructed from depth maps of an ex-vivo rabbit appendix. The policy is then retrained on 849 in-vivo demonstrations from four live rabbits and deployed on four additional live rabbits with electrosurgery armed. With the surgeon selecting the surgical phase, the policy completed the appendectomy in three of the four animals. The results show that demonstrations recorded from a surgeon's own instruments are sufficient to train, select and deploy a bimanual surgical policy in vivo. The robot serves only as the timing reference for sensor calibration and as the executor, and collects no demonstrations. Both demonstration corpora are released to support future surgical robot learning research.

Overview

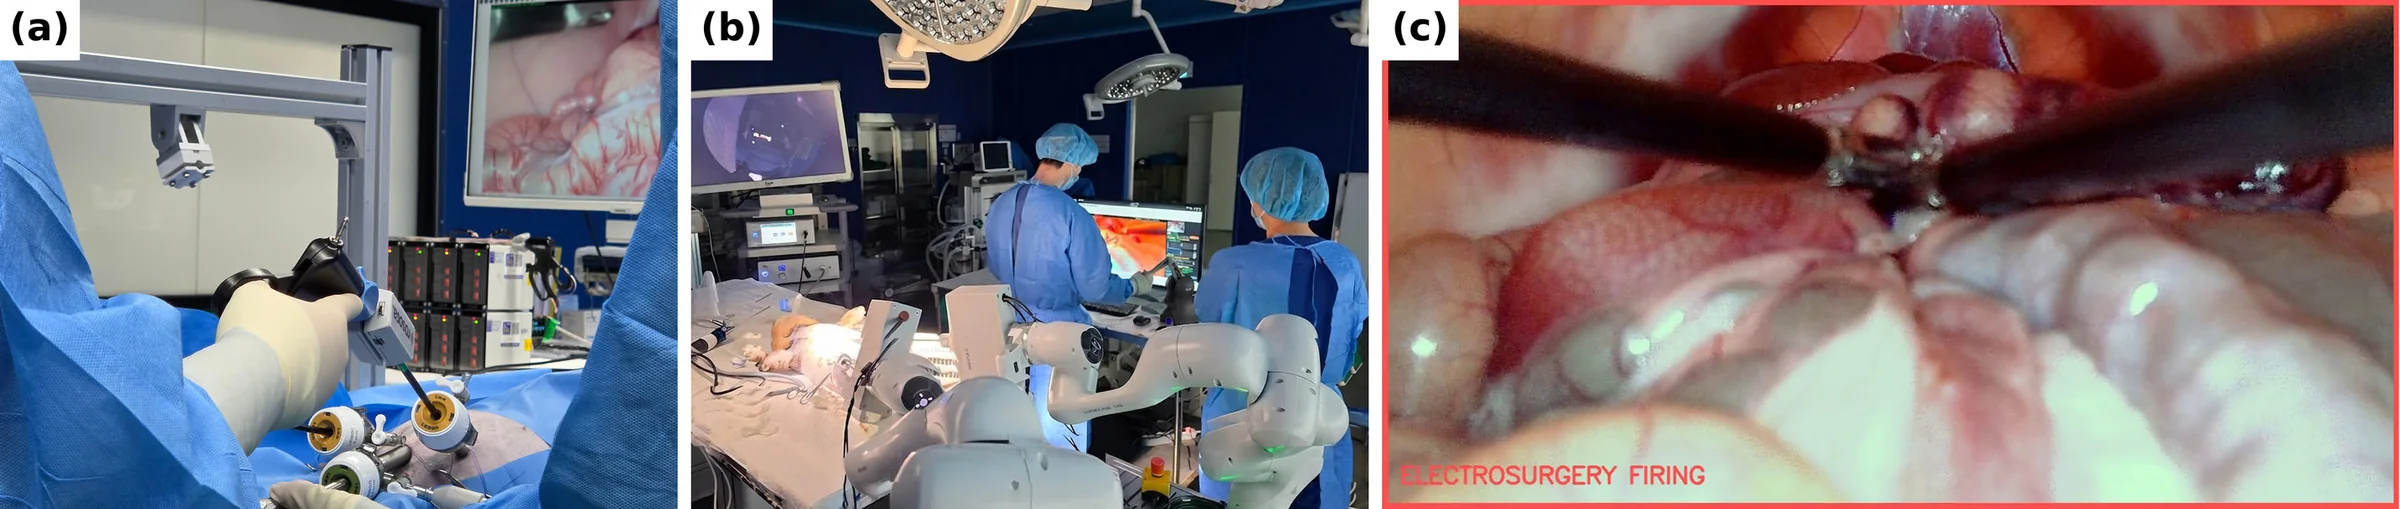
Three panels: a surgeon operating on a live rabbit with a logger on the instrument; two FR3 arms performing the procedure on another rabbit; the endoscope view at the moment of electrosurgery
Figure 1. From hand-held demonstrations to in-vivo robotic execution. (a) A surgeon performs laparoscopic appendectomy on a live rabbit with ordinary hand-held instruments. A shaft-mounted surgical instrument-state logger records the instrument state. (b) The diffusion policy trained on those recordings performs the same procedure on a different live rabbit with two FR3 arms under the surgeon's supervision. (c) Endoscope view during policy control at the moment of electrosurgery. Three of four appendectomies were completed under shared autonomy.

Most minimally invasive surgery is still performed by hand. Robotic surgery is growing, with about 3.15 million da Vinci procedures worldwide in 2025, yet in a US national inpatient sample of 2012 to 2019 admissions three of four minimally invasive abdominal operations were laparoscopic rather than robotic (75.8% vs. 24.2%). On a teleoperated robot such as the da Vinci, the surgeon's instrument motion is recorded as a by-product; in hand-held surgery, everything except the endoscope video is lost when the operation ends. That lost signal is exactly what imitation learning needs.

This paper asks whether the discarded signal of hand-held laparoscopy can be captured in the operating room and turned into a surgical robot policy, and answers it end to end for laparoscopic appendectomy. Our thesis is that a small instrument-state logger on the surgeon's ordinary instrument can stand in for the robot at demonstration time if its channels are synchronized to within one policy step, and that every later stage, from data processing to in-vivo retraining, can be carried out on demonstrations the robot never collected. Our contributions span the entire pipeline:

  1. Surgical instrument-state logger. An operating-room-ready device mounted on the instrument that recovers the full instrument state from an inertial measurement unit (IMU), a time-of-flight sensor and a Hall sensor under the trocar's remote-center-of-motion constraint, and a processing chain built on per-channel latency matching against a robot ground truth. The matching halves the dynamic depth error and, when ablated in closed loop, proves necessary for the lift stage (81% vs. 19%).
  2. A policy configuration selected by closed-loop evidence. Instead of choosing the policy design by offline validation error, we compare 31 candidate designs (backbone, unfreezing depth, phase input, latency matching, replanning) by closed-loop rollouts in a physics simulator built from depth recordings of the ex-vivo scene, score them by stage counts and exact tests, and run only the winner on a two-FR3 rig. A frozen self-supervised ViT backbone removes an order of magnitude of unsafe behavior relative to the standard ResNet-18 encoder, and offline action error turns out to be anti-correlated with closed-loop safety.
  3. In-vivo execution on live animals. The configuration retrained from scratch on 849 in-vivo demonstrations completed the appendectomy in three of four live rabbits under shared autonomy with electrosurgery armed. Ex-vivo pre-training did not change a single in-vivo decision, which is itself the argument for a device that collects in vivo.

We do not claim full autonomy: the surgeon selected the surgical phase because the vision-based phase predictor collapsed under the deployment endoscope. Nor a robot-free pipeline: an FR3 is the ground truth for the latency measurement and the ex-vivo test rig, but collected no training demonstrations.

Method

The surgical instrument-state logger

The surgical instrument-state logger records the pose and jaw opening of a hand-held laparoscopic instrument during real operations, turning the surgeon's own motion into demonstration data. It mounts on the shaft outside the patient, needs no external camera or tracker, and leaves the part that enters the patient untouched. A rigid instrument through a trocar has four degrees of freedom, not six, because the remote-center-of-motion (RCM) constraint removes two. Orientation about the trocar comes from an IMU. The remaining degree of freedom, insertion depth d=ℓ−r, is the shaft length ℓ from the board to the tip minus the board-to-trocar distance r, which a time-of-flight (ToF) sensor pointed down the shaft measures directly. Each instrument therefore carries one board (Seeed XIAO nRF52840) with a BNO085 IMU and a ToF sensor, plus a linear Hall sensor on the handle (WSH137-XPAN1, sampled at 200 Hz) that reads a magnet on the moving handle ring and so measures jaw opening.

Two generations share this principle. The ex-vivo logger (VL53L0X ToF) was powered and read over a USB-C cable and smoothed the depth with an exponential moving average. The in-vivo logger was redesigned for the operating room: a faster ToF (VL53L1X, five-sample moving average, 40 ms), a 1000 mAh lithium-polymer cell and BLE streaming at 50 to 200 Hz, so that no cable leaves the instrument, all housed in a compact enclosure. At the measured draw of about 50 mA the cell lasts roughly 20 h, beyond one operating-room day.

Against the FR3 tip pose during free motion, the latency-matched channels track shaft roll and depression to 0.42° and 0.17° RMS and insertion depth to 1.36 mm RMS once the firmware's fixed gain and offset are calibrated out, and the tip displacement over a 1.6 s action chunk to 1.38 mm RMS (2.89 mm at the 95th percentile). Video-based instrument tracking, for comparison, reaches 2.6 to 3.0 mm at best on public benchmarks and 5.4 to 12.4 mm under occlusion; on our own rig, a markerless fit of the shaft's silhouette edges located the axis only to a median 10.7 mm.

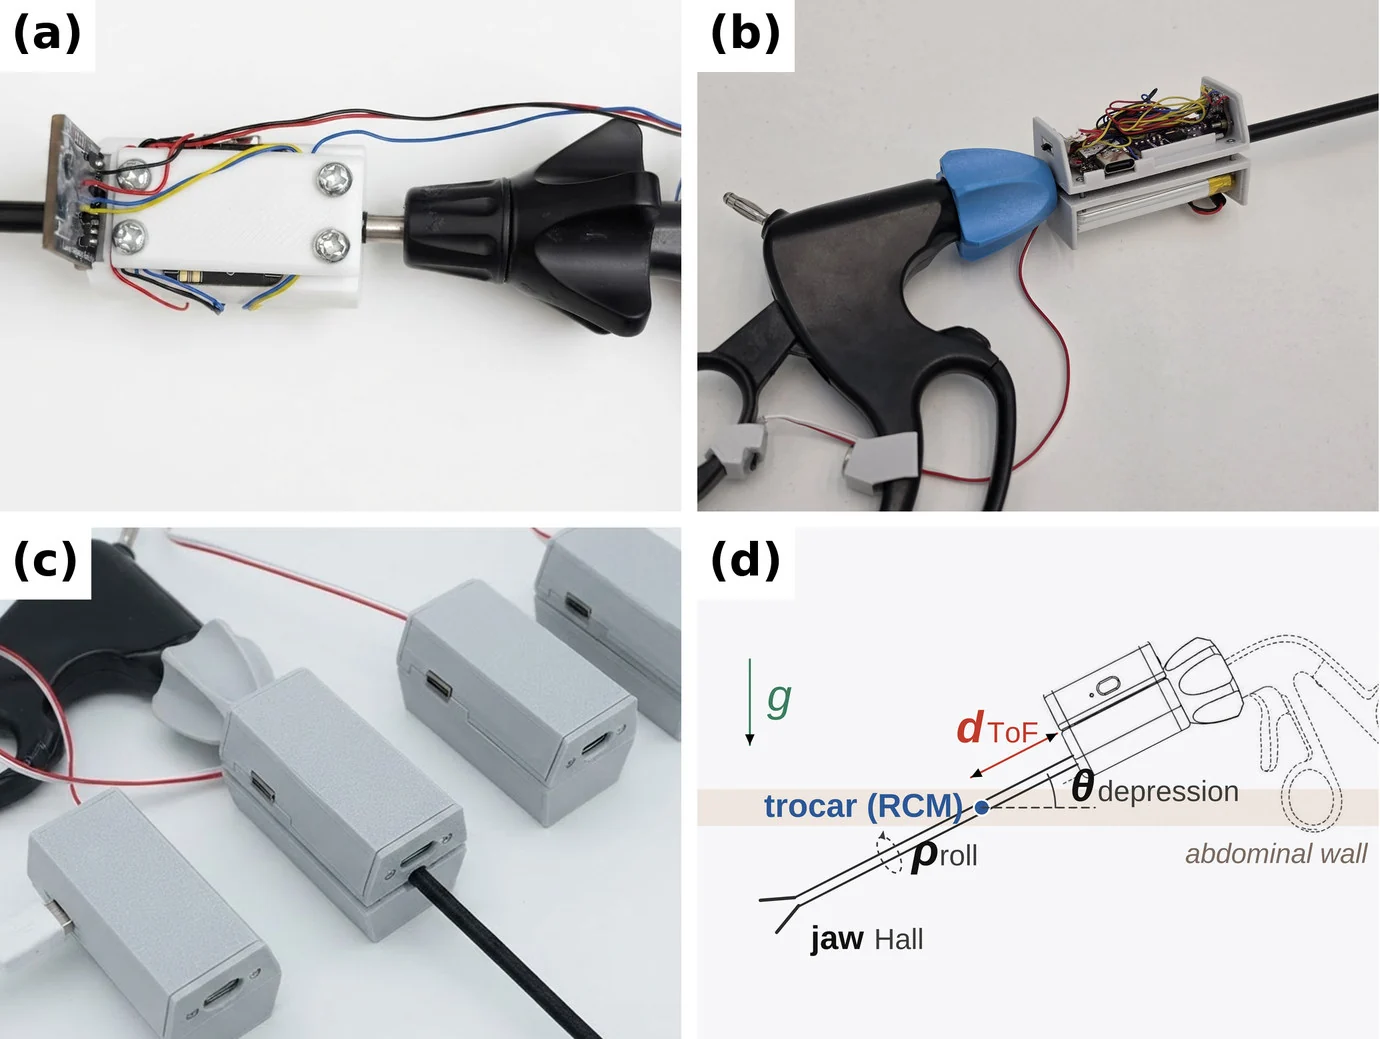
The ex-vivo logger, the in-vivo logger with its enclosure open and components labelled, four in-vivo loggers, and the four-degree-of-freedom geometry through the trocar
Figure 2. The surgical instrument-state logger. (a) The ex-vivo logger on a laparoscopic grasper. (b) The in-vivo logger with its enclosure open: nRF52840 microcontroller, BNO085 IMU, VL53L1X ToF sensor, 1000 mAh lithium-polymer cell and, on the handle, the WSH137 Hall sensor and its magnet. (c) Four in-vivo loggers as used in the operating room: the same sensors in a compact enclosure with no exposed wiring. (d) Geometry: four degrees of freedom through the trocar. Roll ρ and depression θ come from the gravity-referenced IMU, insertion depth d from the ToF ray to the trocar, and jaw opening from the Hall sensor.
A standard laparoscopic grasper with the in-vivo logger on its shaft near the handle

The in-vivo logger on a standard laparoscopic grasper.

Live tracking of the instrument state on a laparoscopic phantom.

Per-channel latency matching

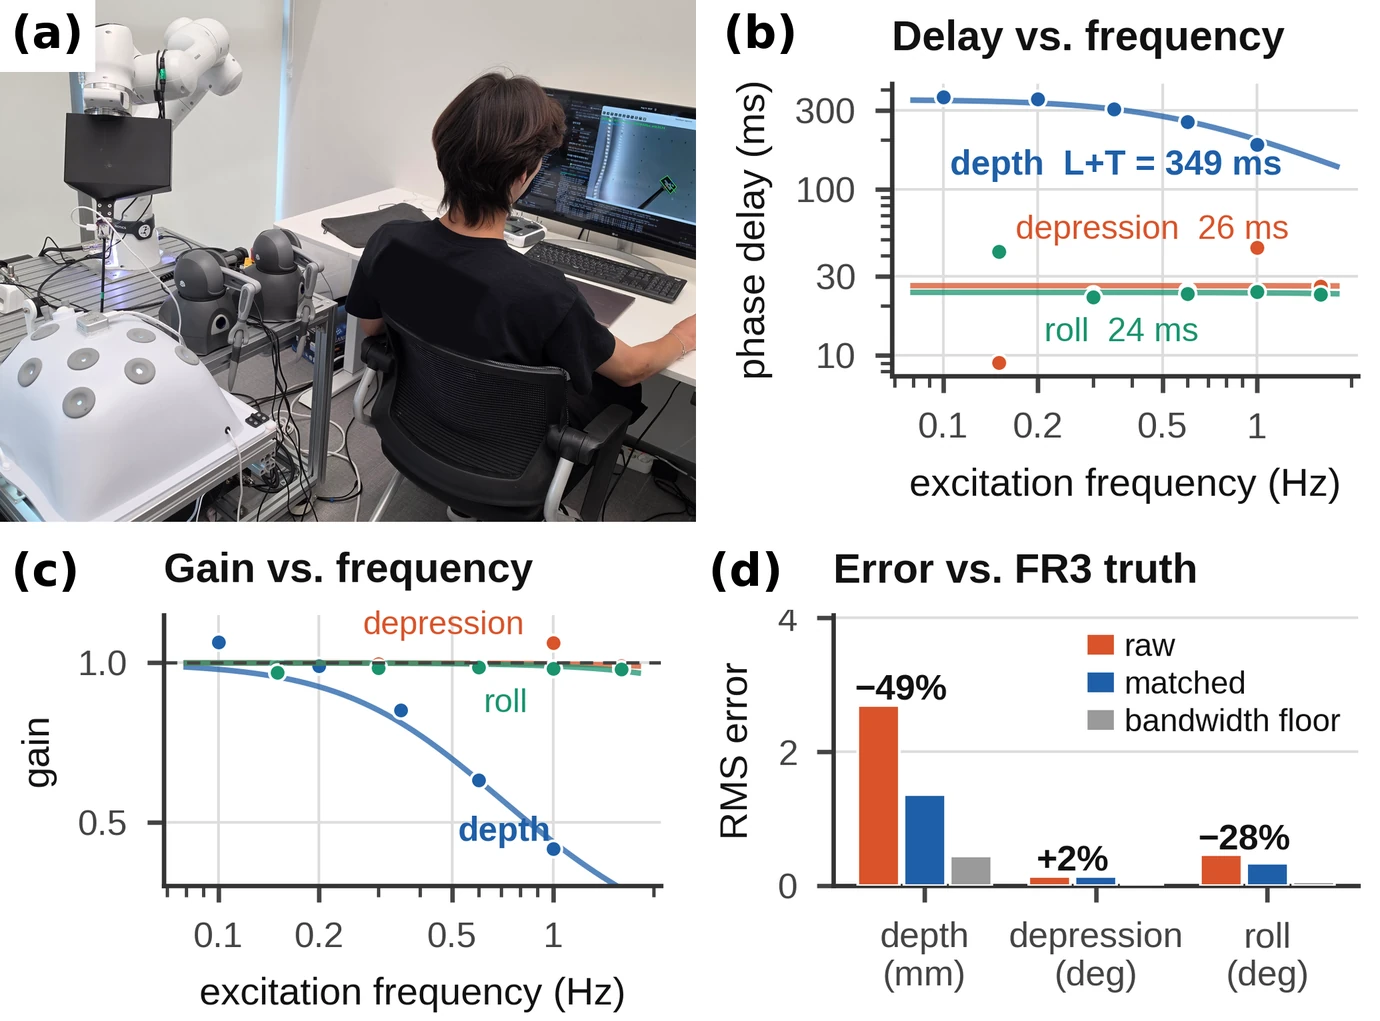
Each channel reaches the log later than the event it describes, by a different amount. A Franka FR3 drove an instrument carrying the logger through the phantom trocar along swept-sine trajectories while its tip pose, published at 200 Hz from the 1 kHz joint state, served as ground truth, and for each channel we fitted the response

H(jω)=e−jωL1+jωT,

where L is a pure transport delay and T the time constant of a first-order lag. The distinction matters: a channel with T≈0 can be corrected by a time shift, one with a large T cannot, because part of the motion is gone.

On the ex-vivo logger the attitude channels showed pure transport delays of 24 to 26 ms, while insertion depth showed L+T=349 ms, 93% of it first-order lag from the firmware's exponential moving average, with gain falling to 0.42 at 1 Hz. The resulting 325 ms depth–attitude skew is 3.5 policy steps at 10 Hz, and no common time shift can remove it. Rewinding each channel by its own latency (−17, +307 and +37 ms for attitude, depth and jaw) cut dynamic depth error from 2.69 to 1.36 mm (−49.5%) and shaft-roll error by 28%. The depression channel, whose 26 ms latency is below what the motion resolves, changed by +2% and serves as the control.

Latency measurement setup, fitted delay and gain per channel against frequency, and dynamic error before and after per-channel rewinding
Figure 3. Per-channel latency. (a) An FR3 drives the instrument through the phantom trocar with swept sines; its tip pose is the ground truth. (b) Fitted delay and (c) gain per channel versus excitation frequency, ex-vivo logger (in-vivo logger: same protocol, values in the paper). Only insertion depth is frequency dependent, a first-order lag rather than a transport delay. (d) Dynamic error before and after rewinding each channel by its own latency; the depression channel is the control.

From logs to training pairs

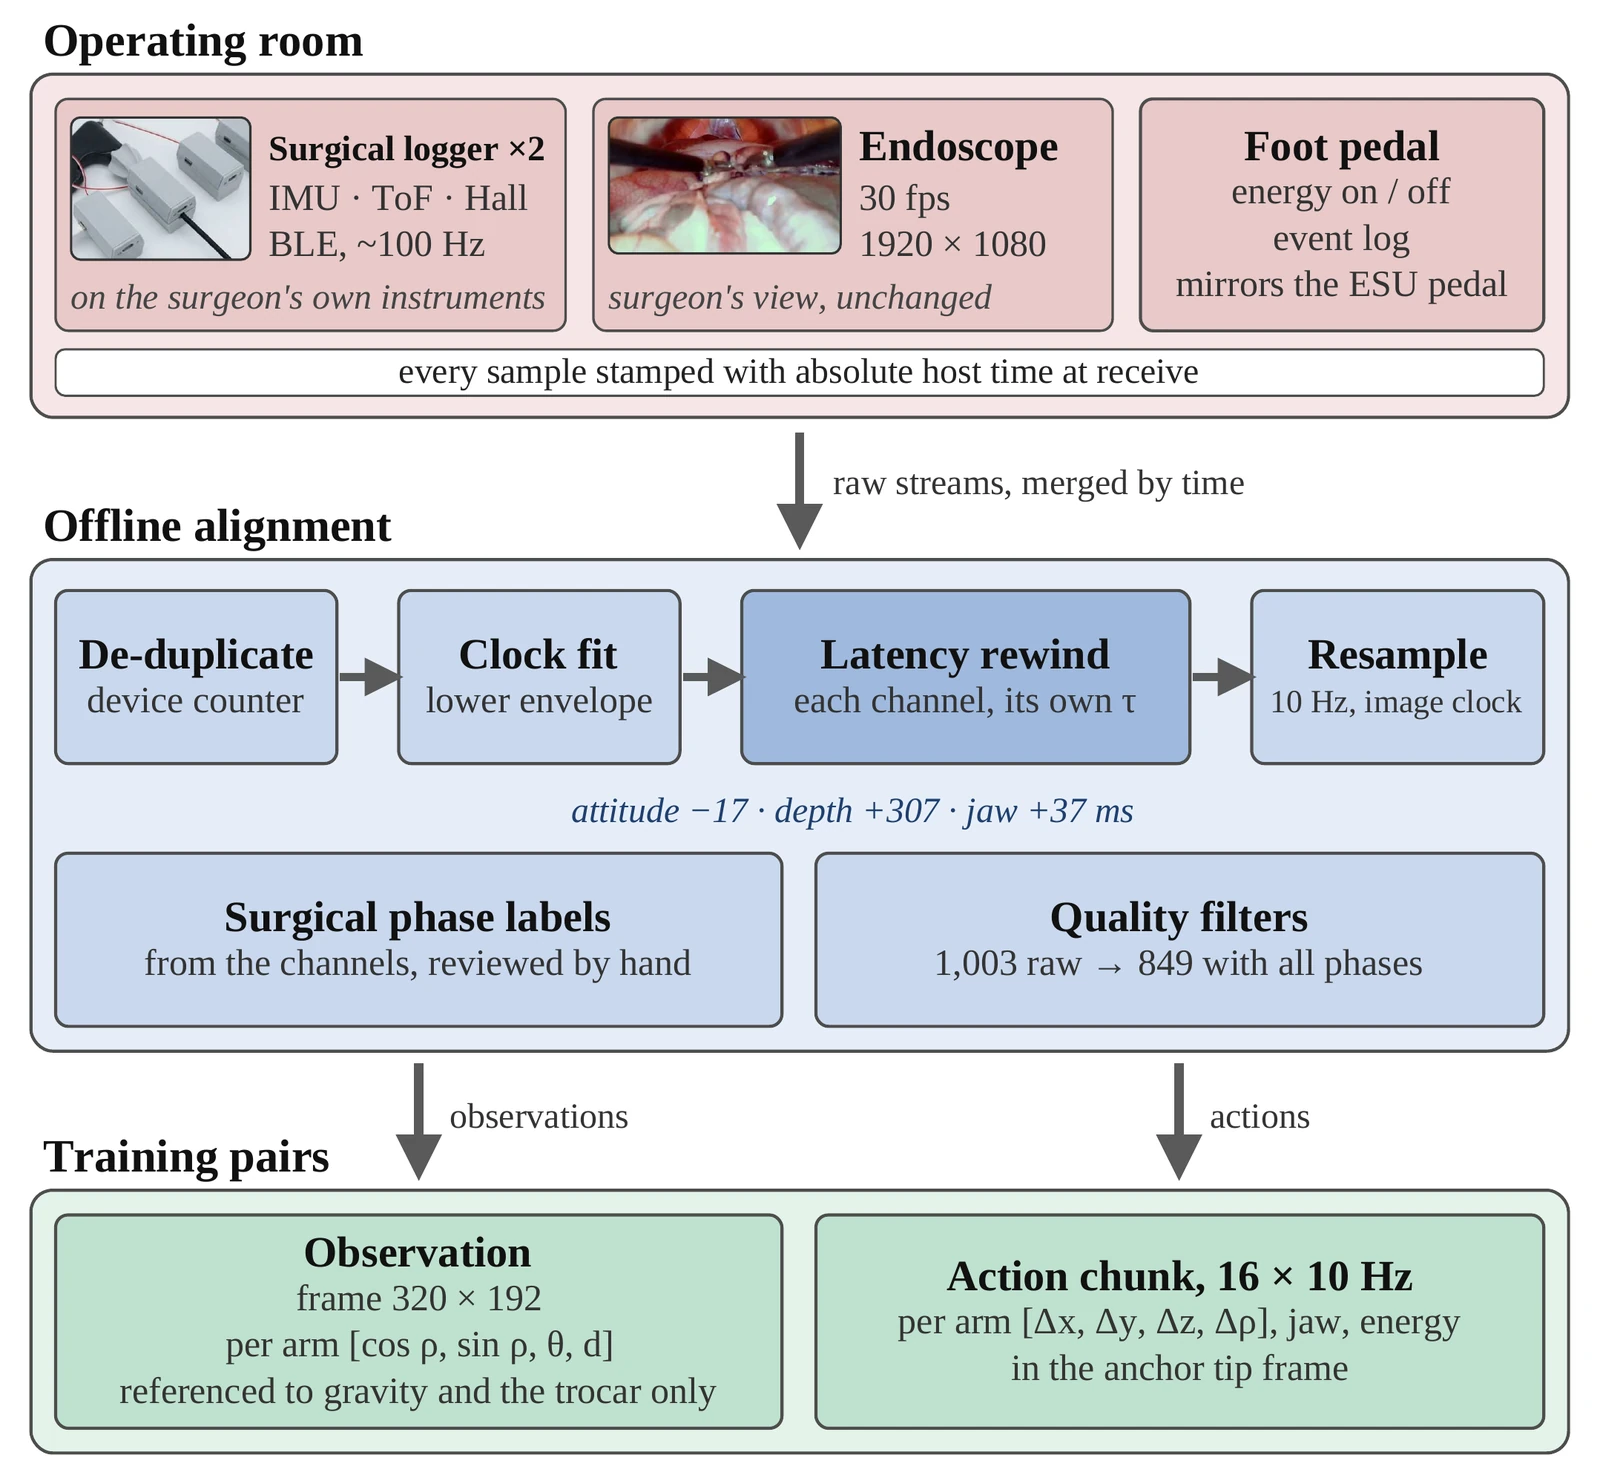
Every recorder, the boards, the endoscope capture and a foot-pedal "energy" channel that mirrors the electrosurgical pedal, stamps each sample with the host's absolute time at the earliest receive point; streams are merged offline by that time, rewound by their own measured latency and resampled on the endoscope clock. The magnetometer heading of a low-cost IMU drifts in an operating room, so the observation uses only what gravity and the trocar define: the endoscope frame at 320 × 192 and, per arm, [cosρ,sinρ,θ,d/dmax]. The jaw aperture is deliberately not an input; with it, the policy learns "it is closed now, so keep closing".

Actions are 16-step chunks at 10 Hz of per-arm tip-frame deltas relative to the chunk's anchor pose, plus absolute jaw aperture and, in vivo, an absolute electrosurgery channel owned by the cutting arm. Because every label is relative to its anchor, it is invariant to the heading zero and to where the trocar sits, so no correspondence between the demonstration trocar and the robot's trocar is needed.

Block diagram of the data pipeline from raw sensor logs through time stamping, latency rewinding and resampling to observation and action pairs
Figure 4. Data pipeline from raw sensor logs to training pairs. Every stream is stamped with absolute time, rewound by its own measured latency and resampled on the endoscope clock. Observations use only quantities referenced to gravity and the trocar, so that magnetometer drift never enters the policy.
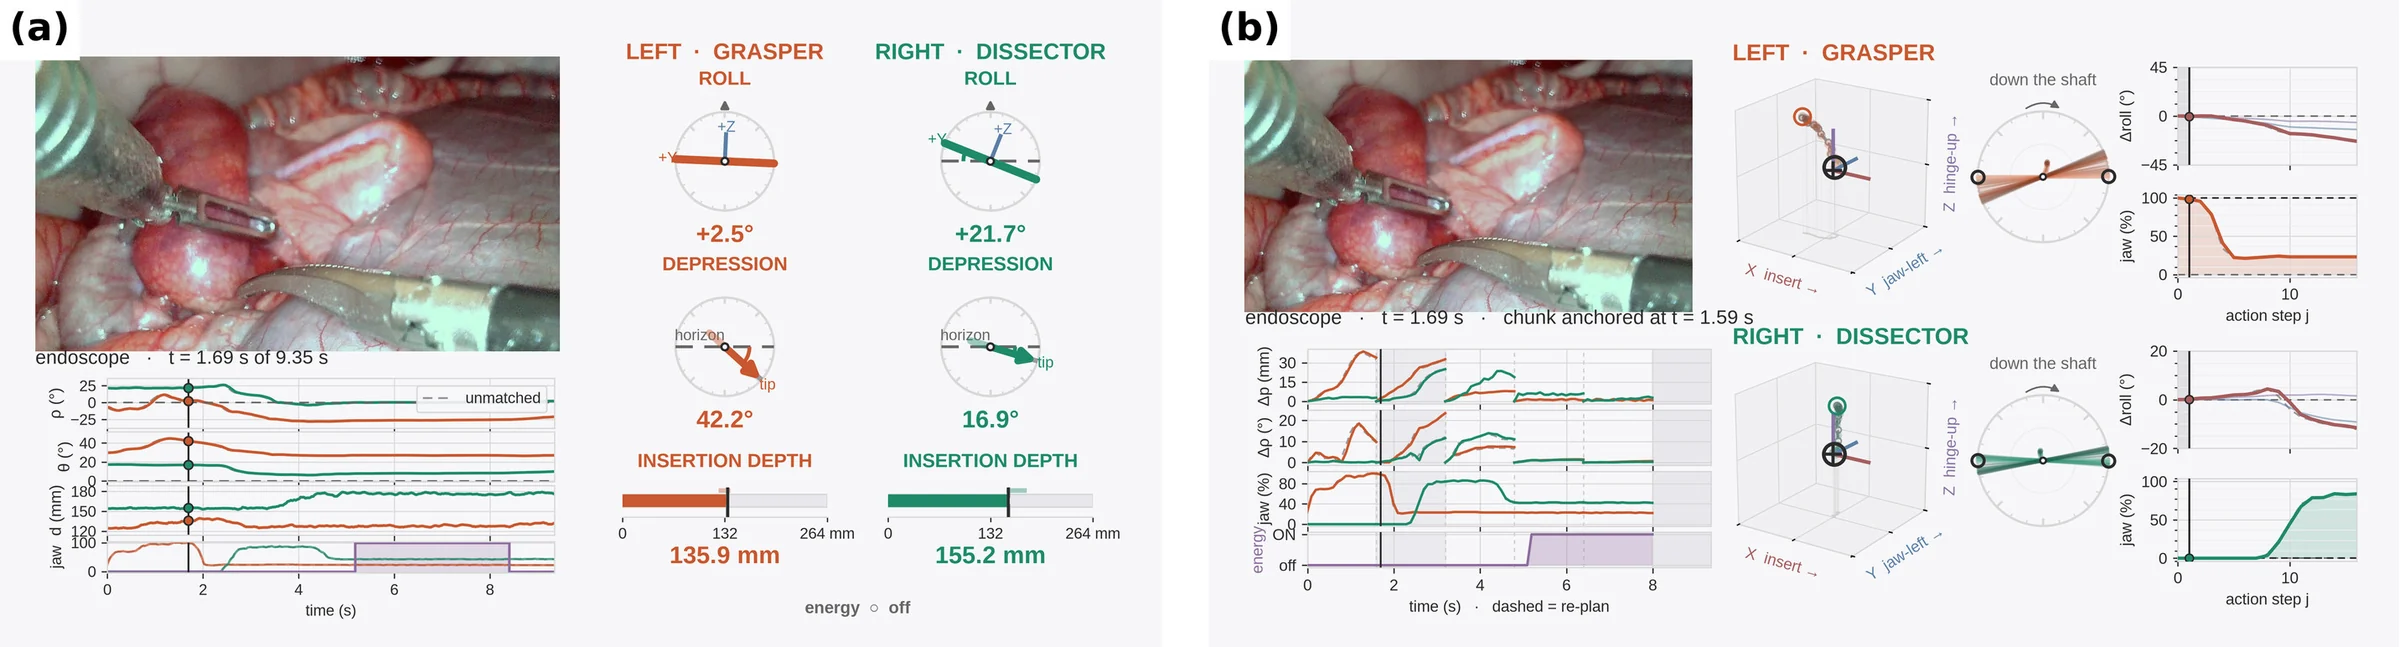
Model input panel with the endoscope frame and per-arm roll, depression and depth, and action chunk panel with each arm's 16-step tip path, roll, jaw and energy channels
Figure 5. Policy observation and action chunk for one in-vivo demonstration at t = 1.7 s, as the grasper closes on the appendix and the dissector approaches. (a) Model input: the endoscope frame and, per arm, shaft roll ρ, depression θ and insertion depth d after per-channel latency matching, as time series and as instantaneous gauges. (b) The action chunk anchored at 1.6 s: each arm's 16-step tip path in its tool frame, the emitted roll (spokes) and jaw channels, and the energy timeline (mauve). All of it was recorded by the surgical instrument-state logger on the surgeon's own instruments.

Policy

The policy is a 1-D U-Net diffusion policy with DDIM sampling over 16-step chunks, with three changes. A single shared DINOv3 ViT-B/16 replaces the two ResNet-18 encoders, with attention pooling and only the last transformer block trainable (7.1 M of 85.7 M parameters). Because the observation window is 0.2 s, the policy cannot infer where in the procedure it is, so the U-Net is conditioned by FiLM on an ordinal encoding of the surgical phase plus two timing channels. And a chunk executor commits three actions per chunk and replans, with the index it starts from absorbing the observation anchor, the arm's measured execution latency and inference.

Simulator and selection protocol

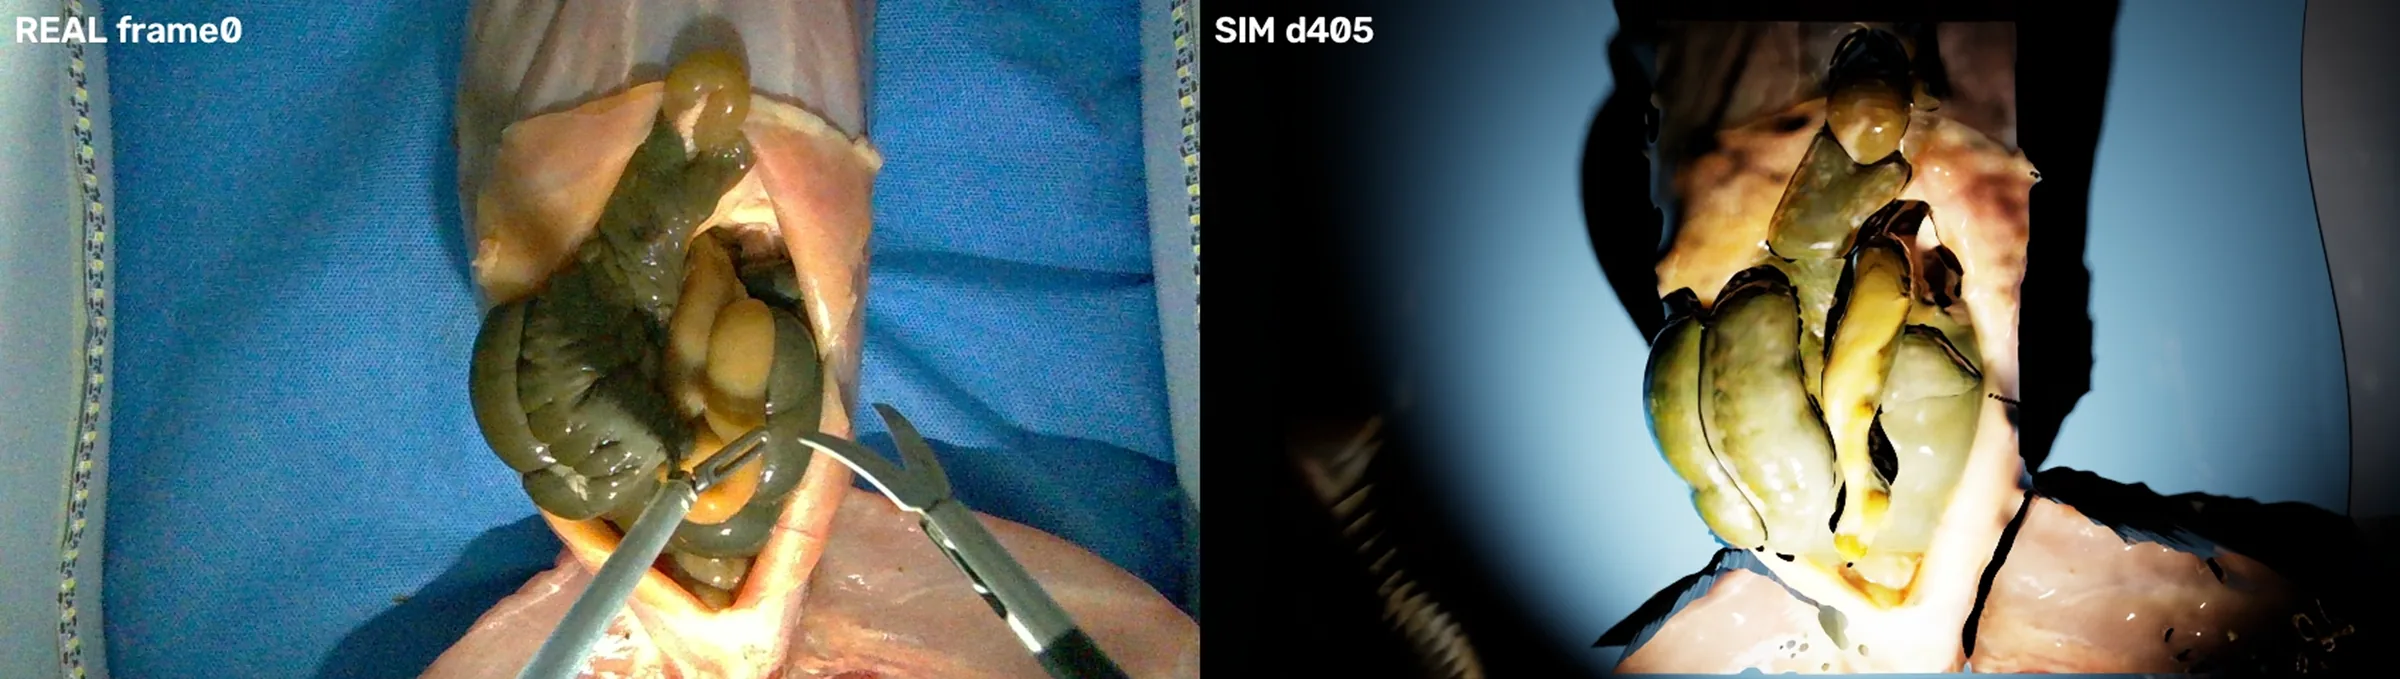
Rather than select the configuration by offline validation error, 31 candidates were compared by closed-loop rollouts in a simulator whose organs are reconstructed from RealSense D405 depth recordings of the ex-vivo scene: 16 episodes of 15 s each, scored on stage counts (lift, arrival at the site, jaw closed on tissue) and on one hard failure, a trocar violation above 10 mm. Because sim-to-real transfer for deformable tissue remains unreliable, the simulator is used to compare configurations under one protocol, and only the chosen one runs on the real rig. The simulator itself is described in a companion paper (see below).

Side by side: the real endoscope frame of the ex-vivo phantom and the simulator's rendering of the organs reconstructed from the RealSense D405 depth map
The real endoscope frame of the ex-vivo phantom (left) and the simulator's organs reconstructed from the D405 depth map (right).

Experiments

Demonstration corpora

Both corpora were captured with the surgical instrument-state logger alone: one unit on the shaft of each instrument streamed its channels to the recording host (over USB ex vivo, over BLE in vivo), which also captured the endoscope and the pedal channel. No marker, external tracker or calibration object entered the field, and the surgeon worked with the instruments as usual. Each episode is one attempt at the procedure. The ex-vivo corpus is 533 episodes on two rabbit cadaver specimens in a laparoscopic training phantom, recorded by two surgeons. The in-vivo corpus comes from four live rabbits in one operating-room session, trocars through the abdominal wall, with a dissector and an electrosurgical unit on the right arm; of 1,003 raw episodes, 849 survive the quality filters.

CorpusEpisodesDurationSetting
Ex-vivo53374 min2 rabbit cadavers in a phantom, ex-vivo logger
In-vivo849135 min4 live rabbits, in-vivo logger, energy pedal

Table I. Demonstration corpora used for training. Each episode is one attempt at the appendectomy recorded with the surgical instrument-state logger on the surgeon's hand-held instruments. Duration is the total recorded time after quality filtering.

Configuration selection on the ex-vivo corpus

Selection criterion. A policy that does nothing never violates the trocar, so violations alone cannot select a configuration; GR00T-H and the frozen backbone score well on it for that reason. The criterion was therefore the full approach without a violation (lift, arrive at the site and close the jaw on tissue), the furthest stage the simulator can score, reached with few violations. On this criterion the DINOv3 configuration with its last transformer block unfrozen was the best of the 31 (81%), ahead of two unfrozen blocks (50%) and of the fully frozen backbone (44%), whose low violation rate comes at the price of never closing the jaw on tissue (grasp depth 0.0 mm). GR00T-H (0%, none of 24 checkpoints closed a jaw on tissue) and ResNet-18 (≤12%) are far behind.

Backbone. Replacing the two ResNet-18 encoders with a frozen DINOv3 reduced trocar violations from 88% to 6% (Fisher p = 7 × 10⁻⁶) and raised lift from 12% to 69% (p = 0.003).

Latency matching. Training the deployed configuration on the same episodes processed without per-channel latency matching leaves trocar violations unchanged (19% vs. 19%) but eliminates successful lifts (19% vs. 81%, p = 0.001), while its validation mean absolute action error (MAE) is better (0.138 vs. 0.148): the 325 ms depth–attitude skew breaks the coordinated insertion that lifting requires, which offline error cannot see.

Unfreezing. Safety degrades as more transformer blocks are unfrozen (violations 6%, 19%, 19%, 56%, 69% for zero to four blocks), while only unfreezing a single block raises the full-approach rate notably above the frozen backbone (81% vs. 44%).

Offline error vs. closed-loop safety. That offline validation error does not predict closed-loop success is known from robomimic; in our surgical setting it goes further and is anti-correlated with safety. Across the unfreezing sweep, validation MAE improves monotonically (0.152 to 0.142) while violations rise from 6% to 69%. The least safe encoder, ResNet-18, even has a better MAE (0.145) than the frozen DINOv3 (0.152).

Run-time phase input and replanning. A phase predictor trained on demonstration video cut the deployed configuration's lift from 81% to 31% and its full approach from 81% to 25%; one trained in the simulator's own domain recovered part of this loss but still halved lift. Committing one action per chunk instead of three raised violations from 19% to 69% and cut the full approach from 81% to 31%.

ConfigurationTrocar violation ↓ [95% CI]Lift ↑Full approach ↑ [95% CI]Grasp depth (mm) ↑MAE ↓
Model
GR00T-H (VLA), no phase12%[3–36]50%0%[0–19]—0.184
DP, ResNet-1888%[64–97]12%12%[3–36]13.90.145
DP, DINOv3 frozen6%[1–28]69%44%[23–67]0.00.152
DP, DINOv3, last block unfrozen19%[7–43]81%81%[57–93]10.80.148
Phase input (fixed: DINOv3, last block unfrozen)
Manual phase19%[7–43]81%81%[57–93]10.80.148
TCN (demo video)50%[28–72]31%25%[10–49]5.20.148
TCN (simulator)25%[10–49]38%38%[18–61]10.30.148
Unfrozen DINOv3 blocks (fixed: manual phase)
None (frozen)6%[1–28]69%44%[23–67]0.00.152
Last 1 block19%[7–43]81%81%[57–93]10.80.148
Last 2 blocks19%[7–43]50%50%[28–72]10.70.146
Last 3 blocks56%[33–77]38%38%[18–61]9.30.143
Last 4 blocks69%[44–86]31%31%[14–56]8.80.142
Latency matching (fixed: DINOv3, last block unfrozen, manual phase)
With19%[7–43]81%81%[57–93]10.80.148
Without19%[7–43]19%19%[7–43]11.00.138
Replanning (fixed: DINOv3, last block unfrozen, manual phase)
nexec = 319%[7–43]81%81%[57–93]10.80.148
nexec = 169%[44–86]31%31%[14–56]10.70.148

Table II. Closed-loop simulator results of the ex-vivo configuration ablation. 16 episodes of 15 s per configuration. Lift and Full approach (the selection criterion) count violation-free episodes. Italic rows name the factor varied and the settings already fixed. Shaded rows mark the setting kept. All rows use latency matching and nexec = 3 unless varied. DP: diffusion policy.

Closed-loop simulator rollouts behind Table II

GR00T-H (VLA), no phase
Violation 12% · Full approach 0%

DP, ResNet-18
Violation 88% · Full approach 12%

DP, DINOv3 frozen
Violation 6% · Full approach 44%

Without latency matching
Violation 19% · Full approach 19%

DINOv3, last 4 blocks unfrozen
Violation 69% · Full approach 31%

DINOv3, last block unfrozen (deployed)
Violation 19% · Full approach 81%

One episode per configuration from the simulator's endoscope recordings of the Table II evaluations, 10 fps, one frame per policy step. An episode ends early when the trocar constraint is violated.

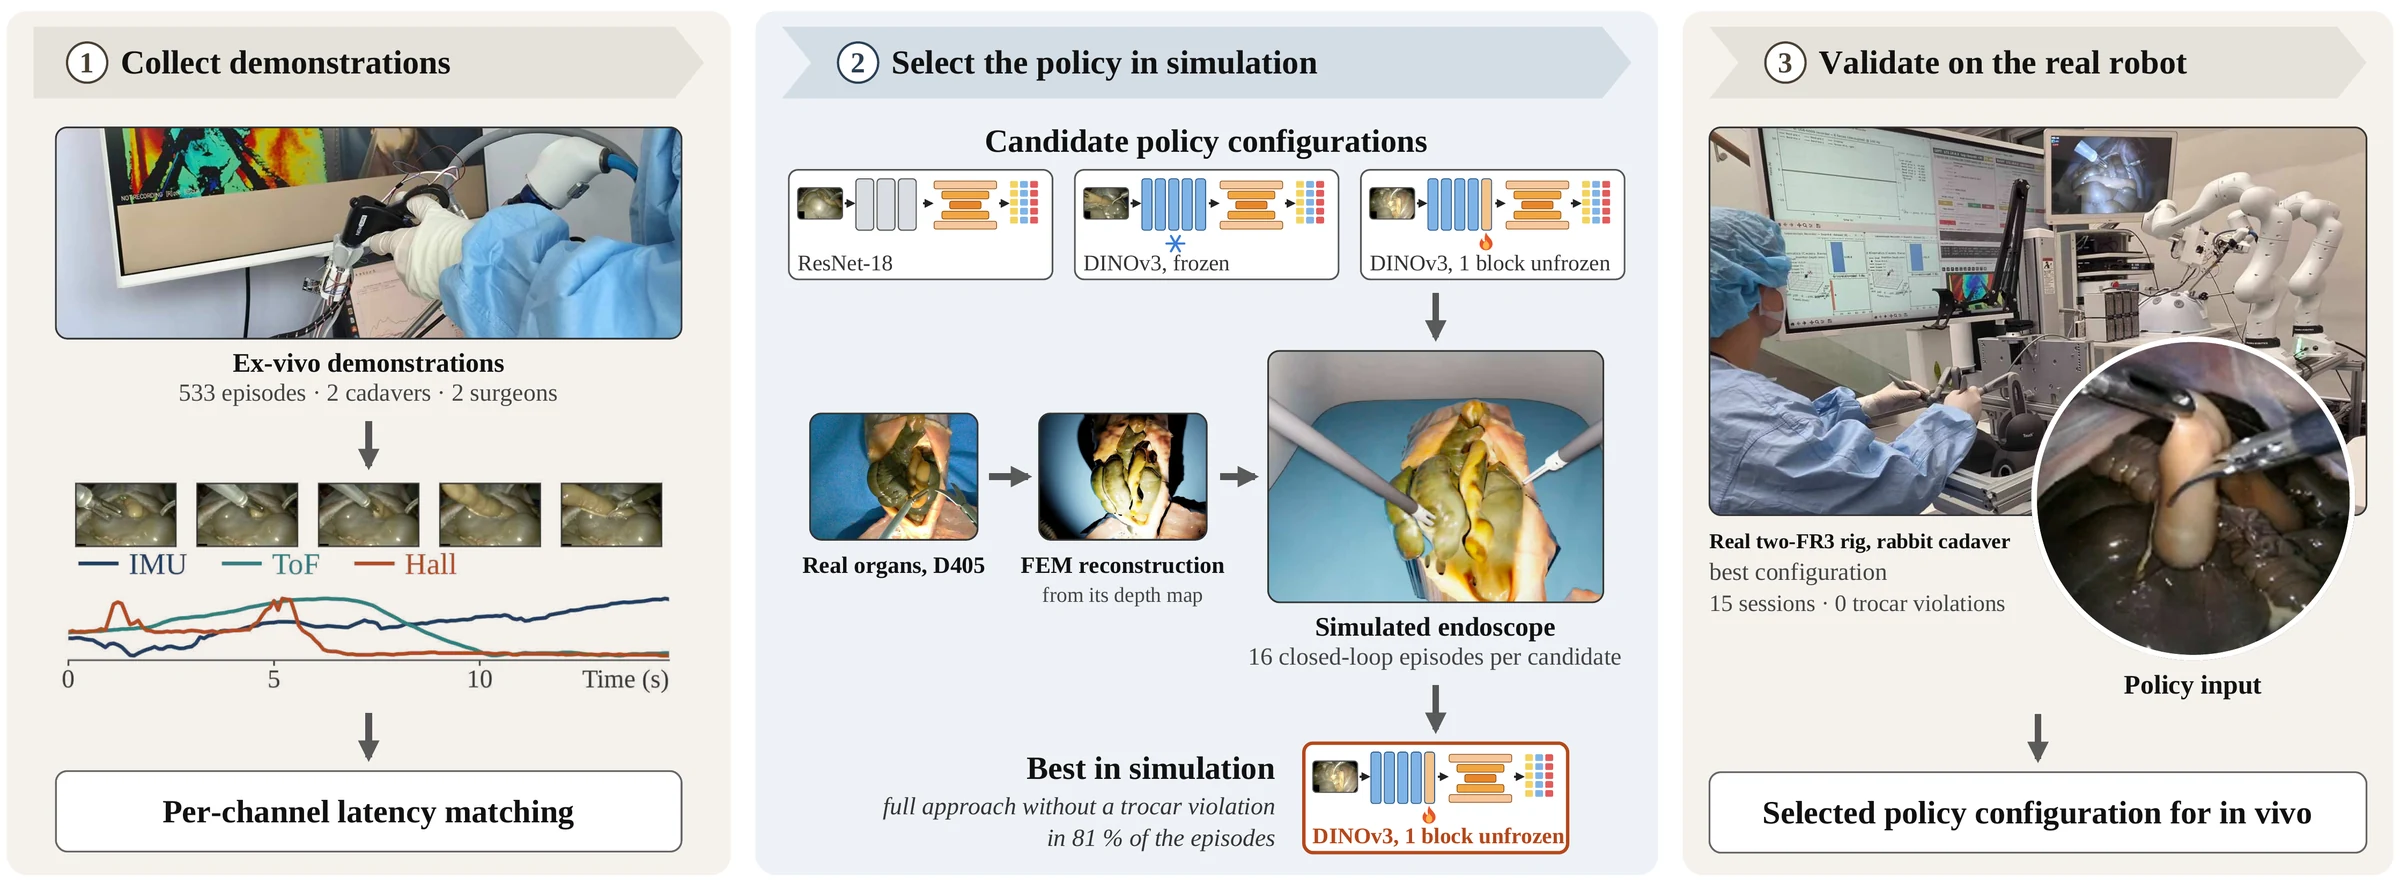
Three stages: demonstrations collected in a laparoscopic phantom, candidate policies run in the reconstructed simulator, and the selected configuration validated on the real two-FR3 rig
Figure 6. Ex-vivo policy selection. Demonstrations recorded with the ex-vivo logger in a laparoscopic phantom (left) train the candidate policy configurations. Every candidate runs closed-loop episodes in a simulator whose organs are reconstructed from the phantom's depth maps (middle). The configuration with the highest full-approach rate without a trocar violation is run on the real two-FR3 rig (right) and becomes the policy configuration retrained for in vivo.

Real ex-vivo rig. The deployed configuration ran on the two-FR3 rig with a rabbit cadaver (15 sessions, about 18 min of policy control): zero trocar violations, peak RCM error 0.23 mm. The phase predictor, however, saturated at the final phase within a median of 10.6 s (rig frames lay outside its training manifold), so in vivo the surgeon set the phase.

The two-FR3 ex-vivo rig: a surgeon at the phase keypress, monitors, and two arms holding instruments through a laparoscopic phantom

The two-FR3 ex-vivo rig.

Endoscope view under policy control on the real rig, rabbit cadaver.

In-vivo training

The policy was retrained from scratch on the 849 in-vivo demonstrations, with the ex-vivo configuration and optimizer-step budget unchanged. Because offline error had already failed as a selector, the checkpoint was accepted through pre-registered event-level gates on unseen episodes: every jaw-closing event detected, energy false-fire 0.019 and missed-fire 0.032 against gates of 0.05 and 0.30, and closed-loop gain 0.86/0.82 against a 0.8 gate.

Ex-vivo pre-training turned out not to matter. Trained from random initialization and from the ex-vivo weights on 25%, 50% and 100% of the corpus, both initializations passed the same gates in all six runs; pre-training helped in offline error only while data were scarce (MAE 1.221 vs. 1.413 at 25% of the corpus, 1.157 vs. 1.173 at 100%). A policy for live tissue has to be trained on live-tissue demonstrations, which is the argument for an instrument that can collect them in the operating room.

Deployment on live rabbits

In-vivo demonstration collection, 30 August 2026.

Policy deployment on a different animal, 4 September 2026.

On a single day the policy ran on four live rabbits at 5 Hz with electrosurgery armed. Inference on one RTX 4090 took a median 23.5 ms per step (95th percentile 59.7 ms), well inside the 200 ms control period. In each animal the surgeon placed the instruments, checked the hand-over state against the demonstration band, handed control to the policy, supplied the phase by keypress, and could take control back at any moment.

In three of the four animals a single rollout carried the instruments from grasp approach to the energized cut without the surgeon touching them. In the fourth the left arm was handed over in a poorly conditioned inverse-kinematics branch and the joint-limit governor aborted before the policy could act; the procedure was completed by hand. All four animals survived, with no gross abnormality during a week of observation.

Safety. Across all policy-controlled time that day the RCM error never exceeded 0.84 mm against a 5 mm abort threshold, and every sample that did exceed the threshold in the day's logs occurred under human teleoperation. In every sample of cautery under policy control (108 samples at 10 Hz) the cutting jaw was closed, with aperture at most 0.7%.

Rabbit 1Rabbit 2Rabbit 3Rabbit 4
Appendectomy completedyesyesyesno‡
Policy control time (s)34.216.814.7—
Cautery fired by policy (s)4.63.03.2—
Peak RCM error (mm)0.200.210.84—
Hand-over channels in demo band6/64/64/6—
Post-operative survival (days)7/77/77/77/7

Table III. Deployment results on four live rabbits. The policy performed one rollout in each animal, and every value is taken from that rollout's log. ‡ Aborted at hand-over by the joint-limit governor (controller, not policy). Completed by hand.

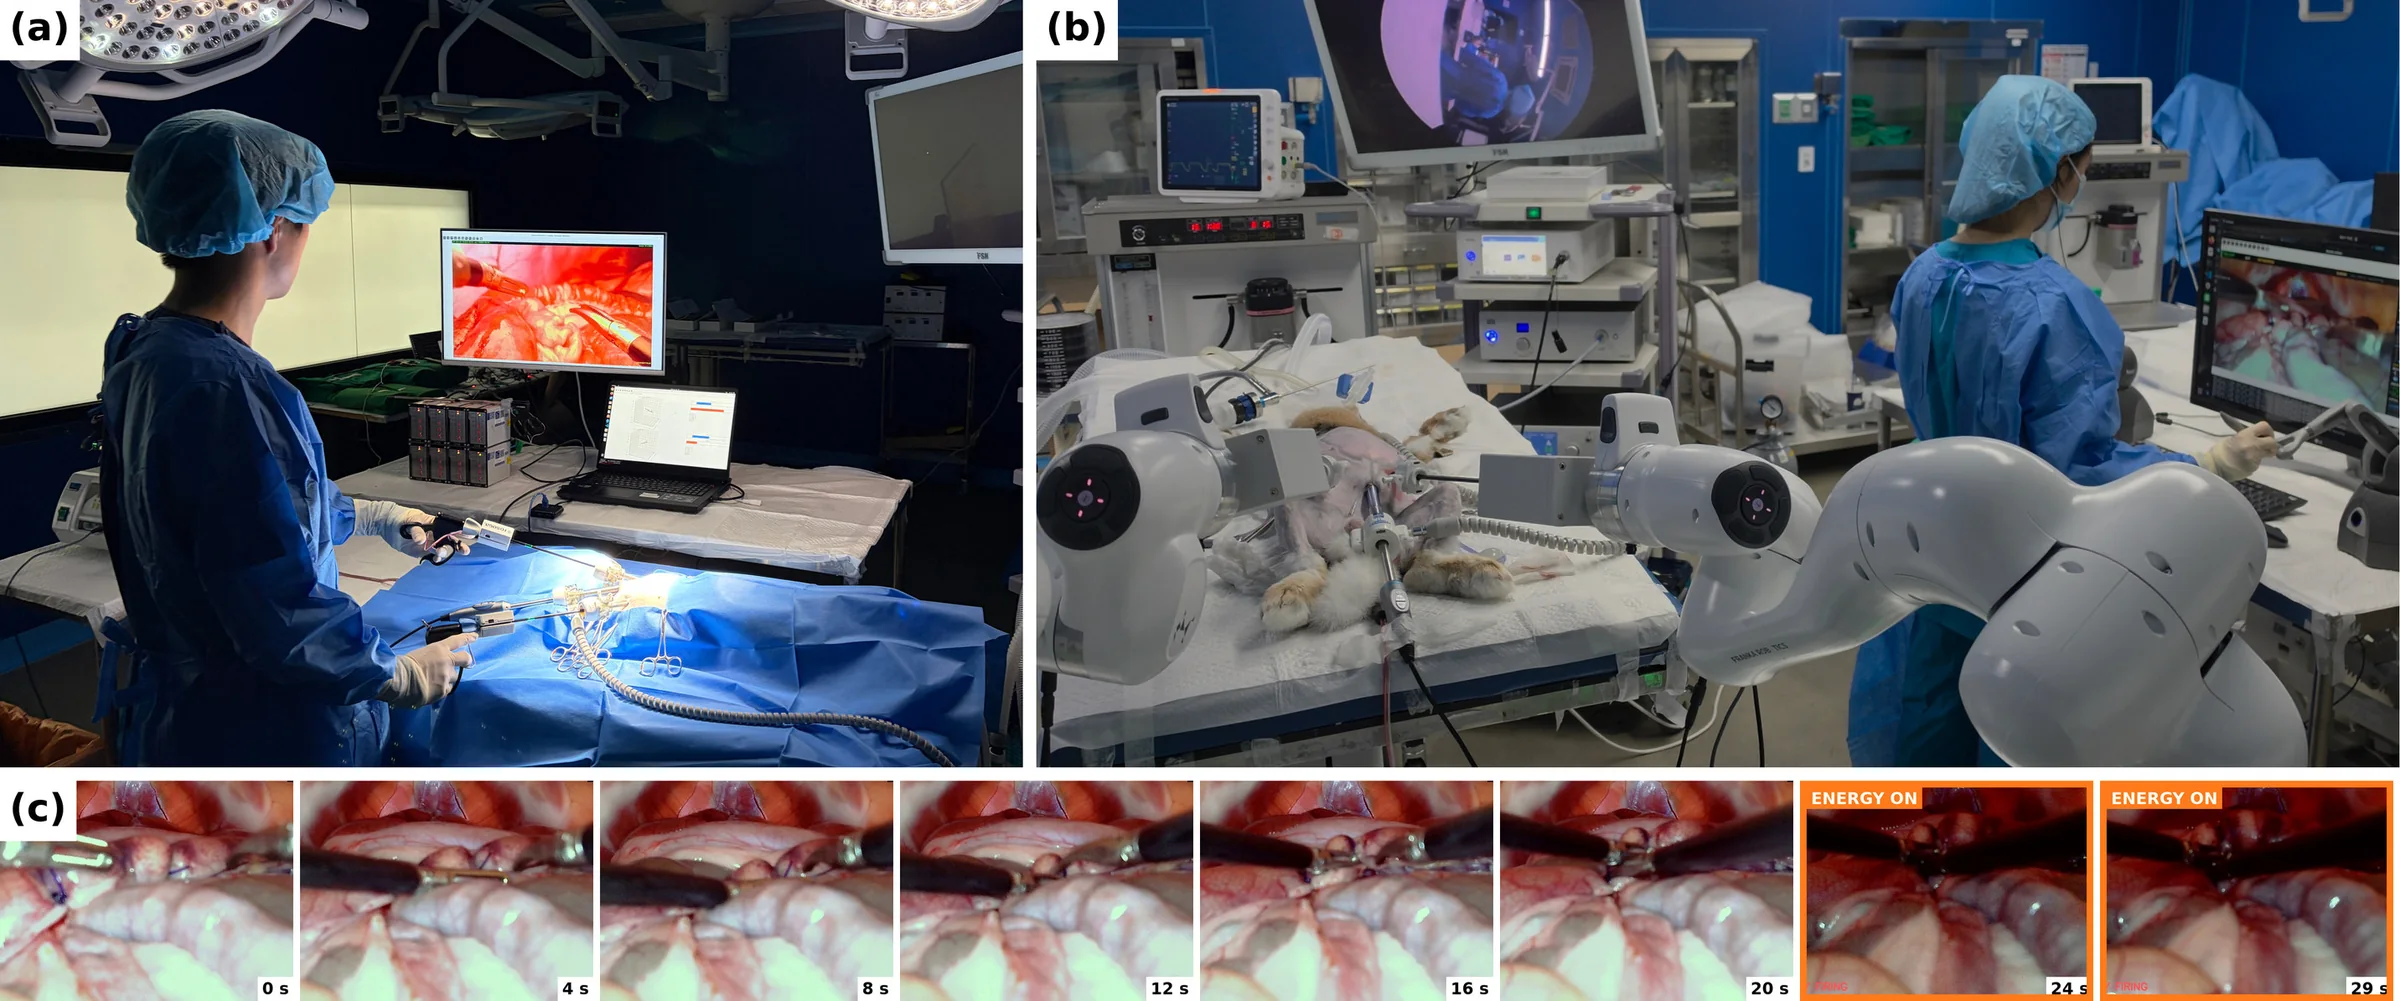
In-vivo demonstration collection, deployment with two FR3 arms, and a strip of endoscope frames from rabbit 1's rollout ending in the energized cut
Figure 7. In-vivo demonstration collection and deployment. (a) In-vivo demonstration collection: the surgeon operates on a live rabbit with instruments carrying the in-vivo logger. (b) Deployment on a different animal: two FR3 arms hold the grasper and dissector through trocars in the anesthetized rabbit with the electrosurgical unit connected. The surgeon supervises at the console. (c) Frames from rabbit 1's 34 s policy rollout: grasper approach, lift, dissector approach, jaws closing on tissue, and the energized cut (orange frames, 24 to 29 s).

Discussion and limitations

A shaft-mounted surgical instrument-state logger with per-channel latency matching turned hand-held laparoscopic demonstrations into a bimanual policy that was selected in simulation, validated on a real rig and executed electrosurgery in live animals. Per-channel latency matching halved the dynamic depth error against the FR3 ground truth (2.69 to 1.36 mm) and raised lift in closed loop from 19% to 81% of episodes. Closed-loop rollouts of 31 candidate configurations identified the policy design: a frozen DINOv3 backbone reduced trocar violations from 88% to 6% relative to ResNet-18, unfreezing its last block gave the highest full-approach rate (81%), validation error improved as safety degraded, and the selected configuration ran on the real rig without a trocar violation. Retrained on 849 in-vivo demonstrations, the configuration completed the appendectomy in three of four live rabbits under shared autonomy, with the cutting jaw closed at every cautery sample and a peak RCM error of 0.84 mm.

This study has two limitations. First, the surgeon supplied the phase in vivo, because the vision-based phase predictor agreed with the surgeon on only 24.6% of policy control steps under the deployment endoscope, a domain shift known from phase recognition across hospitals. Second, due to the complexity of experiments on live animals, the in-vivo study was limited to demonstrations from four rabbits and one deployment in each of four others on a single day.

Eight live rabbits were used in total, four for demonstrations and four for deployment. All animal procedures involving rabbits were approved by the BIOSTEP Institutional Animal Care and Use Committee (IACUC S26-BZ-0562).

Data release

Both training corpora are released in their recorded form, not as derived training arrays. Every stream carries absolute host timestamps (Unix epoch, UTC) so that the per-channel latency matching of the paper can be reproduced or replaced. File layouts, channel definitions, label vocabularies and known issues are documented in the data repository README.

CorpusContentSizeLink
Ex-vivo, logger + endoscopeLogger H5 per arm, 4K 60 fps endoscope clips, overhead camera, force channels, hand-corrected phase labels (585 episodes recorded, 533 used)≈ 61 GBHugging Face
Ex-vivo, RealSense D405ROS 2 bags used for the simulator reconstruction; not needed to reproduce any result in the paper≈ 487 GBpart 1 · part 2
In-vivo, preprocessed episodes868 episode folders: endoscope video with per-frame timestamps, two logger files, pedal state and phase labels (849 used)≈ 46 GBHugging Face

BibTeX

@article{yee2026instrument,
  title   = {From Instrument-Mounted Demonstrations to In-Vivo Execution: Learning Bimanual
             Laparoscopic Appendectomy Without Robot-Collected Demonstrations},
  author  = {Yee, Dongho and Oh, Juahn and Lee, Jinseok and Lee, Jiyul and
             Seo, Yechan and Jeong, Seong and Kim, Minsung and Shim, Seonho and
             Noh, Younghoon and Choi, Hyuk and Kong, Youngbin and Lee, Kyu Eun and
             Kong, Hyoun-Joong},
  journal = {arXiv preprint arXiv:2609.25625},
  year    = {2026},
  url     = {https://arxiv.org/abs/2609.25625}
}